Forefoot & lesser toes
Plantar Plate Injury
Plantar plate injuries are a common cause of pain under the ball of the foot, usually at the base of the second toe. Most people are treated without surgery. This page explains what the plantar plate is, how the injury is diagnosed, the non-surgical treatments Mr Hester most often recommends, in particular toe taping and calf stretches, and when surgery is considered.
Key points
- The plantar plate is a strong ligament under the toe joint. It stops the toe drifting upwards.
- Typical symptoms are pain and swelling under the base of the second toe, sometimes with the toe starting to drift or lift.
- Early treatment, before the toe has moved out of position, gives non-surgical care the best chance of working.
- The main treatments are taping the toe down, offloading the forefoot with stiff-soled shoes and padding, and stretching tight calf muscles.
- Recovery is gradual and is measured in weeks to months, not days.
What is the plantar plate?
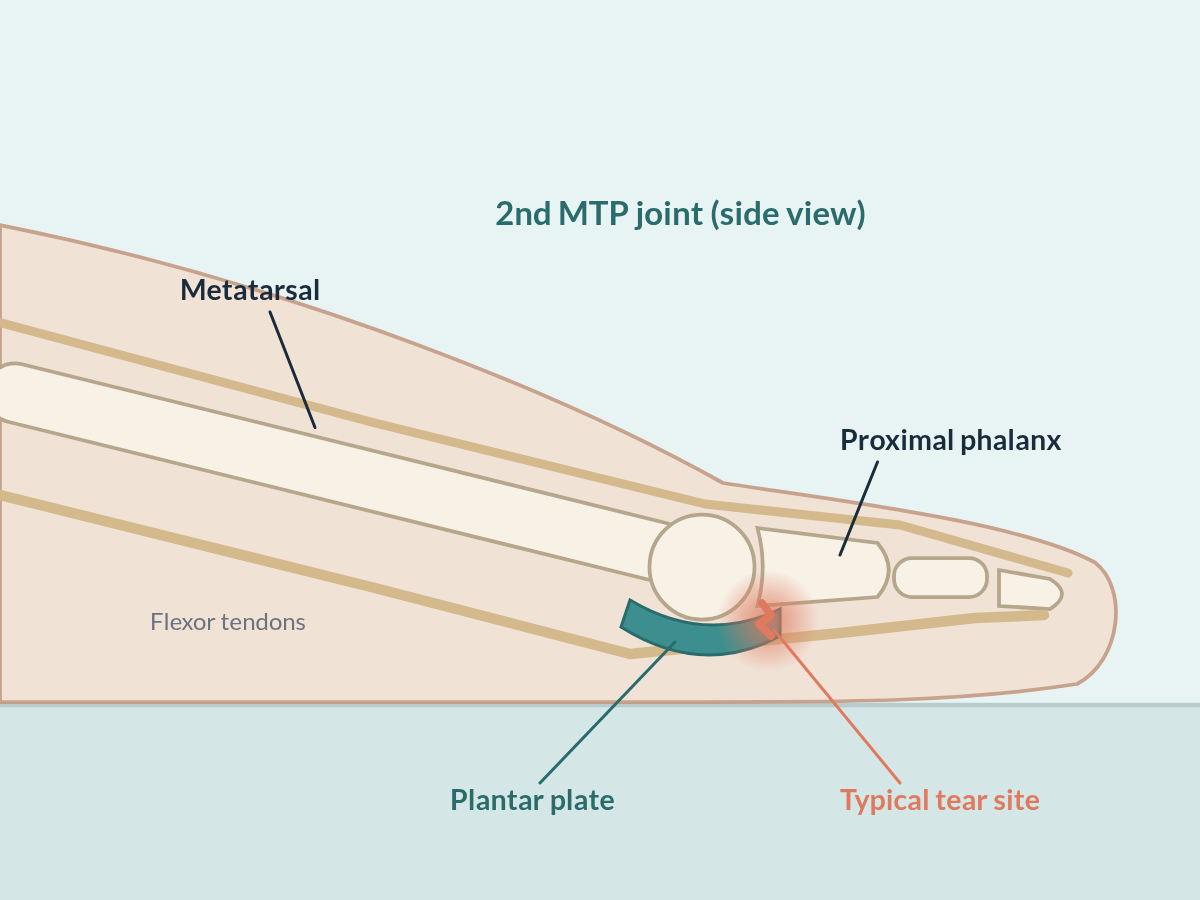
The plantar plate is a thick, tough band of fibrocartilage on the underside of each of the smaller toe joints, the metatarsophalangeal (MTP) joints at the ball of the foot. It is attached firmly to the base of the toe and more loosely to the end of the metatarsal bone behind it. Its job is to support the joint, cushion the ball of the foot and, importantly, stop the toe from bending upwards too far or drifting out of line.
The second toe is the most commonly affected. Problems usually develop gradually from repeated overload rather than a single injury, although a sudden forced upward bend of the toe can also cause a tear. Factors that increase the load on the joint include a long second metatarsal, a bunion, high-heeled or very flexible footwear, a tight calf, and activities that put a lot of weight through the forefoot.
Symptoms
- Pain under the ball of the foot, at the base of the second (sometimes third) toe
- Pain that is worse when walking barefoot, pushing off, walking uphill or wearing heels
- Swelling around the base of the toe, which may be visible on the top of the foot as well as underneath
- A feeling of walking on a pebble or a fold in your sock
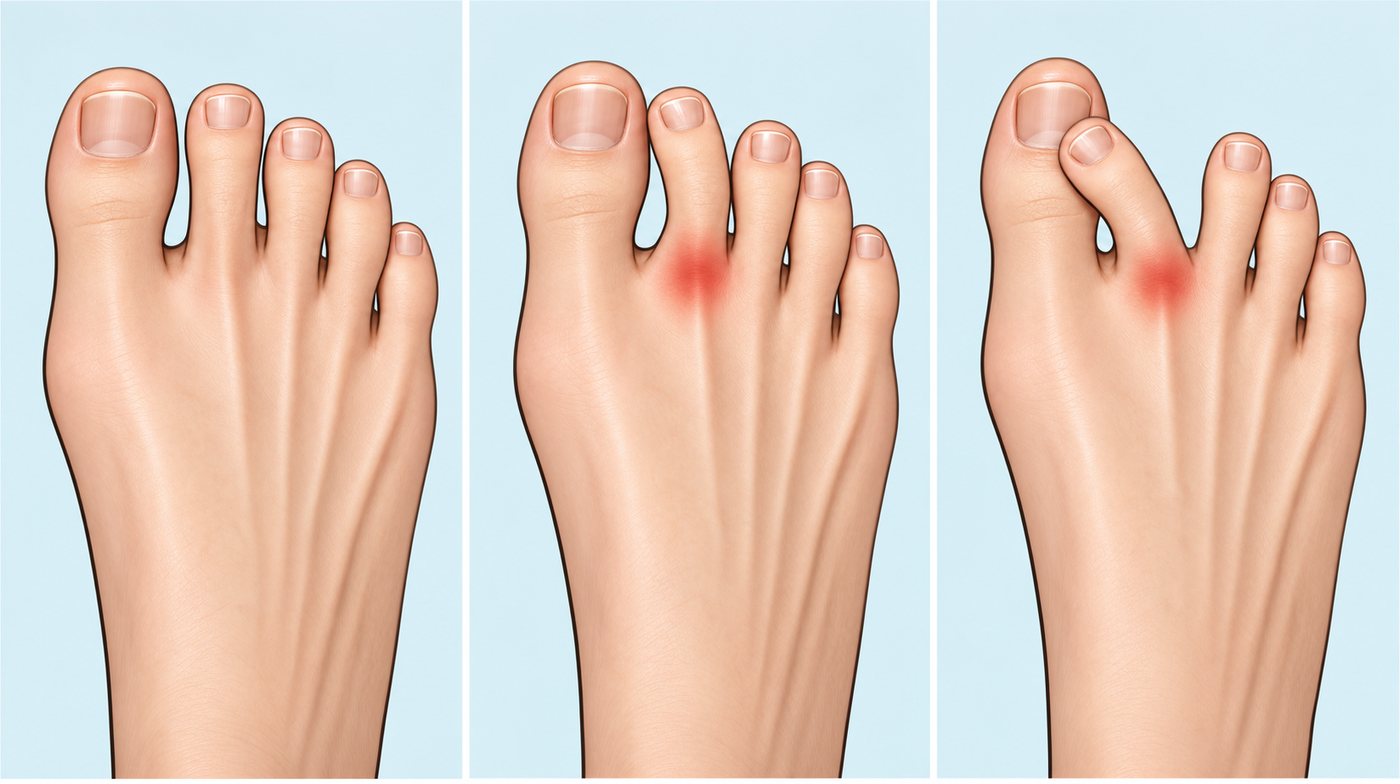
- The toe starting to drift towards the big toe, opening a gap between the second and third toes (sometimes called the "V sign")
- The toe lifting so that it no longer touches the ground when standing
- In longer-standing cases, the second toe may cross over the big toe (a crossover toe)
Similar pain can be caused by other forefoot problems, including metatarsalgia, Morton's neuroma, Freiberg's infarction and stress fractures, which is why an accurate diagnosis matters.
Diagnosis
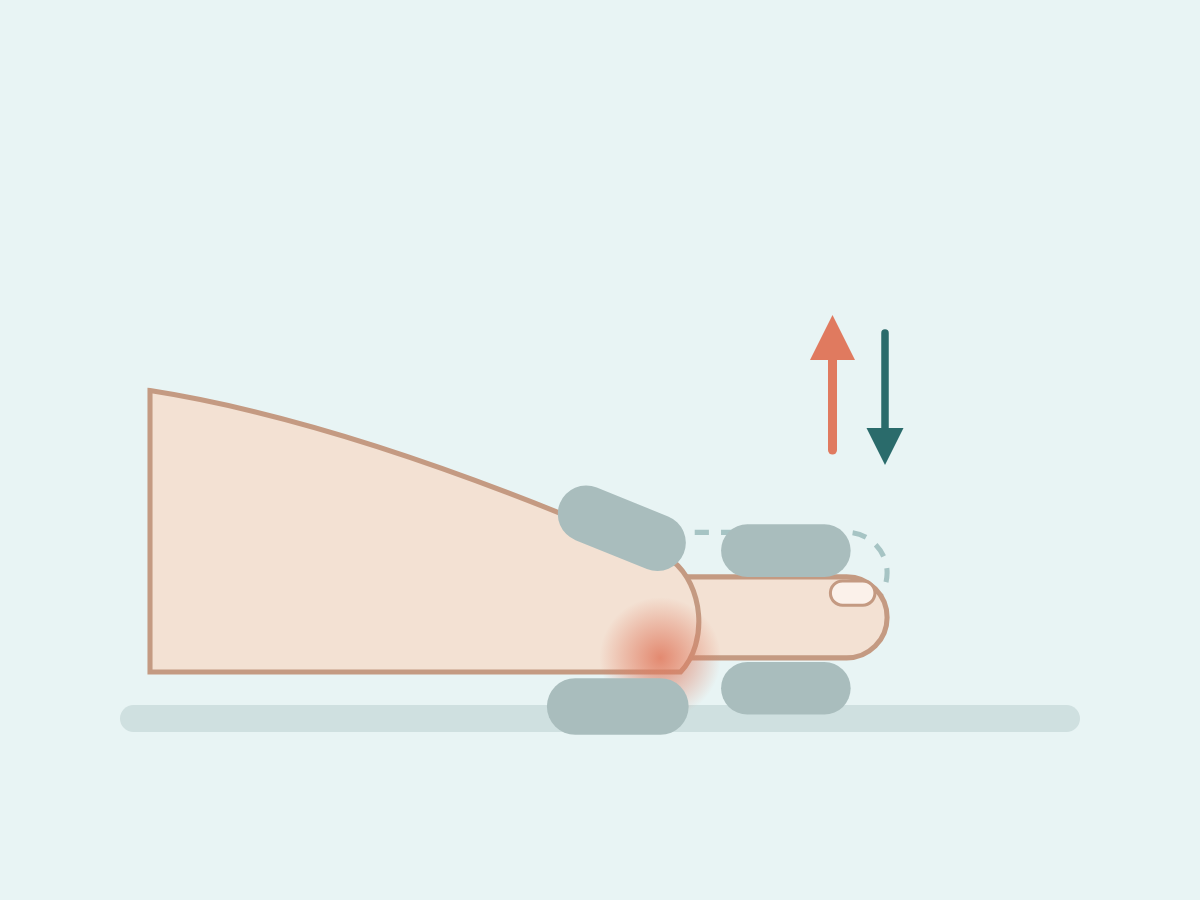
Clinical examination. Mr Hester will examine the foot standing and sitting, check the position of the toes and feel for tenderness directly under the joint. A key test is the vertical stress (drawer) test, sometimes called the Lachman test of the toe: the metatarsal is held steady while the base of the toe is gently moved up and down. Excess movement compared with the other toes, or reproduction of the pain, suggests the plantar plate is damaged. Calf tightness is also assessed, as it increases pressure on the forefoot.
X-rays. Weight-bearing X-rays show the alignment of the toes, the relative length of the metatarsals and any arthritis, and help rule out bony causes such as a stress fracture or Freiberg's infarction.
Ultrasound or MRI. Ultrasound (which can assess the joint while it moves) or MRI is used to confirm a plantar plate tear, judge its size and look for other causes of pain such as a neuroma or joint inflammation.
Non-surgical treatment
The aims of non-surgical treatment are to settle the pain, reduce the load on the injured plantar plate, hold the toe in a good position while it heals, and correct contributing factors such as a tight calf or unsupportive footwear. Treatment works best when it is started early and followed consistently.
1. Toe taping (plantar plate strapping)
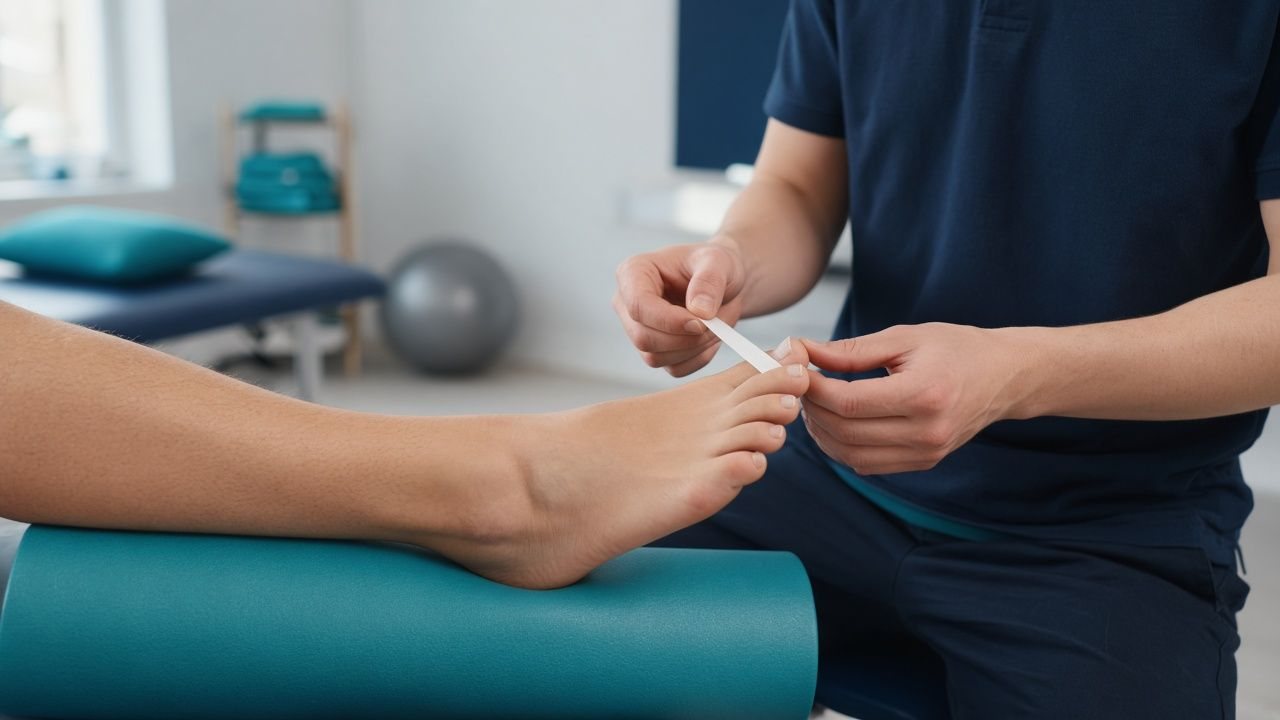
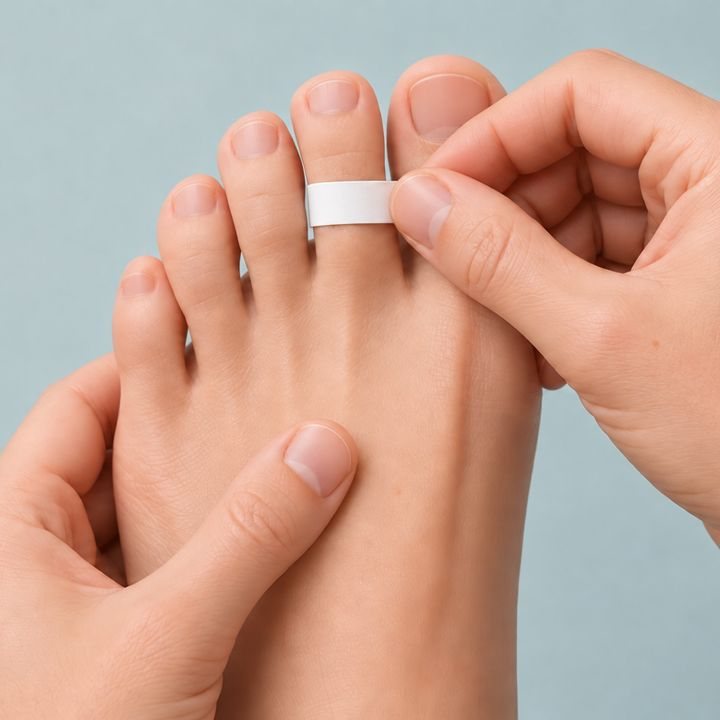
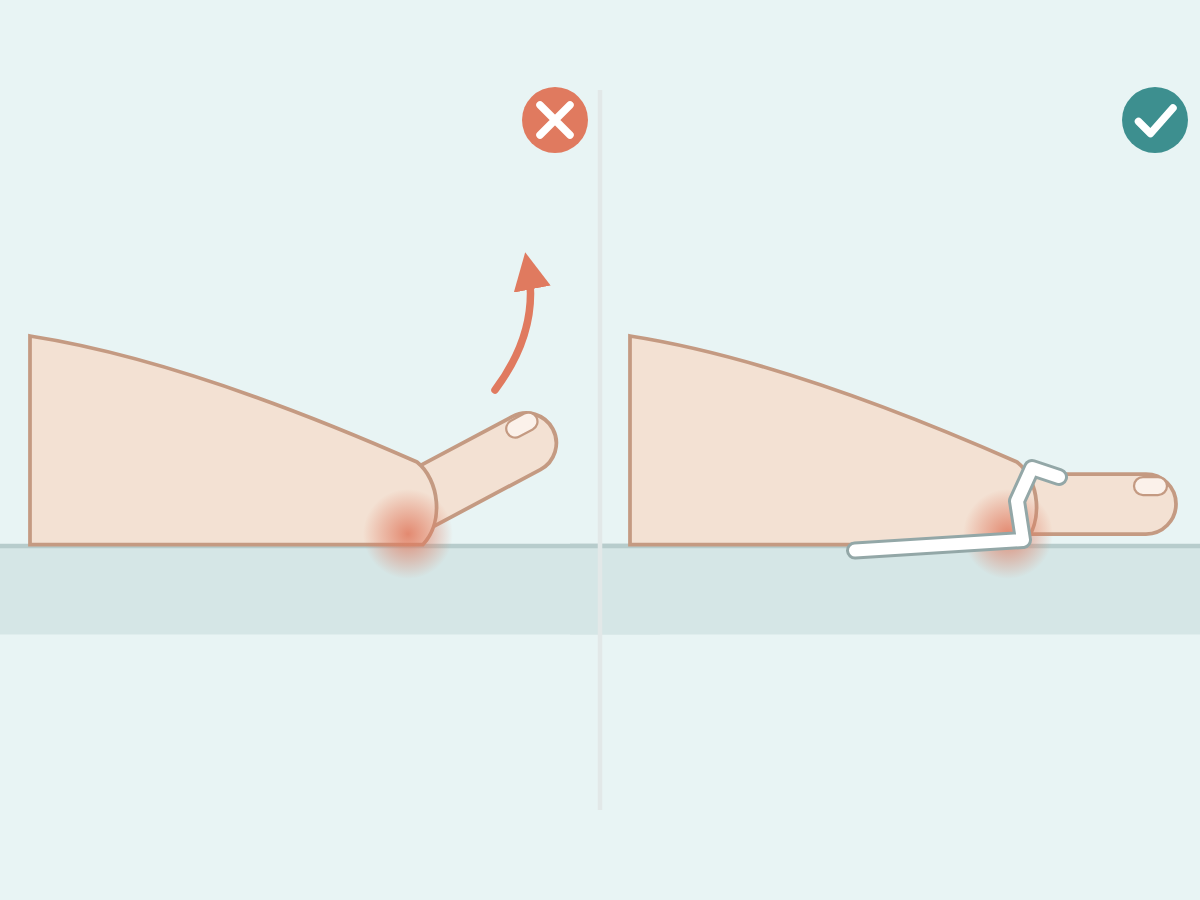
Taping holds the second toe pointing slightly downwards (plantarflexed), in line with the other toes. This takes tension off the plantar plate, reduces pain when pushing off and helps stop the toe drifting upwards or sideways while the tissue heals. Your clinician or physiotherapist will usually show you how to do it the first time.
Illustrative image.
You will need: rigid sports tape (zinc oxide tape) cut into a narrow strip about 1–1.25 cm wide and roughly 20–25 cm long. Method 2 also needs a wider strip (about 2.5 cm) to anchor it. Skin should be clean and dry. Sit with the foot resting comfortably and the ankle relaxed.
Any rigid zinc oxide tape of the right width will do. As an Amazon Associate, thomashester.com earns from qualifying purchases. See also Equipment & Devices.
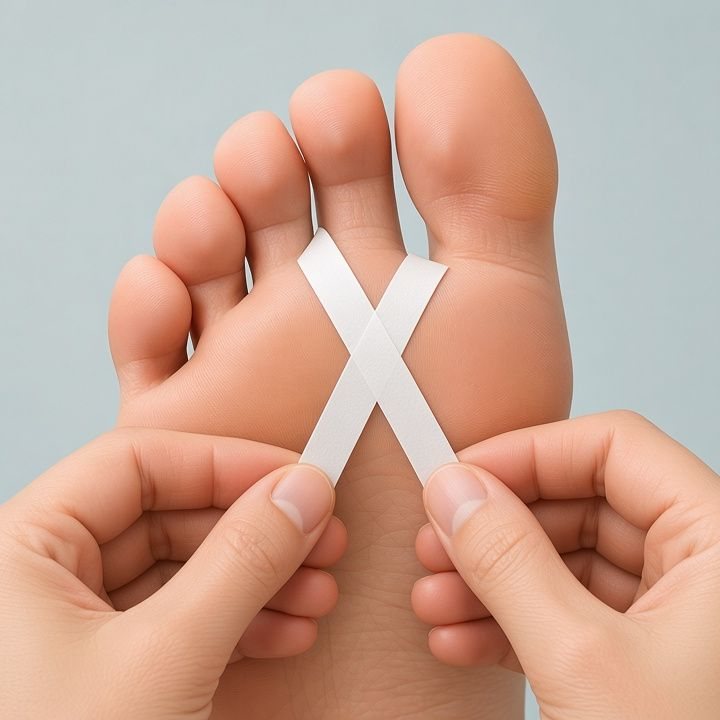
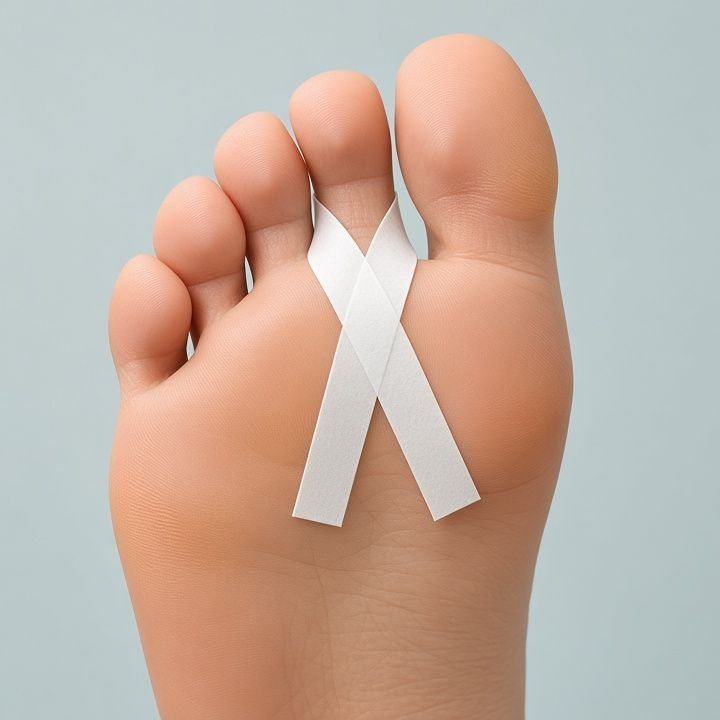
There are two common ways to tape the toe, shown below. They are alternative techniques: use one or the other, not both. Your clinician will advise which suits you.
Method 1: Crossover taping
A single narrow strip loops over the top of the second toe and the ends cross in an "X" (figure-of-eight) under the base of the toe.
Illustrative images.
Method 2: Loop and anchor (two tails) taping
The same loop over the toe, but the two tails run straight back along the sole side by side and are held in place with a wider anchor strip.


Illustrative images.
Taping tips & safety
- Change the tape every two to three days, or sooner if it becomes wet, loose or uncomfortable.
- The tape should feel snug, not tight. Remove it straight away if the toe becomes pale, blue, cold, numb, tingly or more painful.
- Check the skin each time you change the tape. Stop if you develop a rash, blistering or broken skin.
- If you have diabetes, reduced feeling in your feet, poor circulation or fragile skin, please seek advice before taping.
- Ready-made toe straps or splints (for example a Budin-type splint) do a similar job and may be easier to use for some people.
- Taping is usually continued for several weeks while the joint settles. Mr Hester or your physiotherapist will advise how long is right for you.
2. Calf and foot stretches (posterior chain)
A tight calf limits how far the ankle bends upwards. When walking, the body makes up for this by rolling onto the forefoot earlier and harder, which increases pressure on the ball of the foot and the plantar plate. Stretching the two calf muscles, the gastrocnemius (stretched with the knee straight) and the soleus (stretched with the knee bent), is a simple and important part of treatment.
How to stretch
- Stretch to a gentle, steady pull in the calf. It should not be painful, and it should not hurt the ball of the foot.
- Hold each stretch without bouncing.
- Consistency over weeks matters more than stretching hard.
- Wear supportive shoes for standing stretches, so that the painful forefoot is protected.

Wall calf stretches
Knee straight (gastrocnemius). Stand facing a wall with your hands on it. Step the leg to be stretched back, keeping the knee straight, the heel on the floor and the toes pointing forwards. Bend the front knee and lean towards the wall until you feel a stretch in the upper calf of the back leg.
Knee bent (soleus). From the same position, bring the back foot a little closer to the wall and bend the back knee, keeping the heel down. You should feel the stretch lower in the calf, nearer the Achilles tendon.

Towel or band stretch
Sit with your leg straight in front of you. Loop a towel or exercise band around the ball of the foot (not over the toes) and gently pull the foot towards you, keeping the knee straight. This is a useful option if standing stretches are uncomfortable.

Lying towel stretch
Lie on your back with one knee bent. Loop a towel or band around the ball of the other foot, raise the leg and straighten the knee, gently drawing the foot towards you until you feel a stretch in the calf and back of the thigh. Hold, then lower the leg slowly.
Illustrative images.
Step stretch
Stand on a step holding a rail or wall for balance. Position your feet so that the edge of the step is under the arch, not under the painful ball of the foot. Slowly lower the heels until you feel a stretch, hold, then rise back to level. Leave this one out if it causes forefoot pain.
Your physiotherapist may also add gentle strengthening exercises for the small muscles of the foot once pain allows.
3. Footwear, padding and other measures

Rocker-soled shoe
A stiff, rocker-soled shoe lets the foot roll through each step without bending the toe joints.
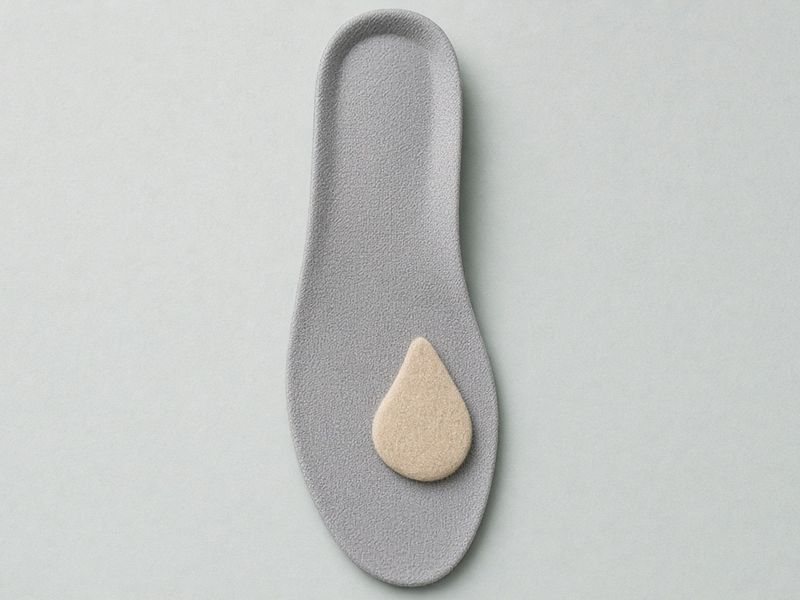
Metatarsal pad
A metatarsal pad sits just behind the painful joint, not directly under it.
Illustrative images.
- Stiff-soled or rocker-soled shoes. A firm sole that does not bend at the ball of the foot, or a curved "rocker" sole, reduces how much the toe joints bend with each step. A stiff insole or carbon-fibre plate can achieve a similar effect in some shoes.
- Metatarsal pad. A small dome-shaped pad placed just behind the ball of the foot spreads the load away from the injured joint. If it sits directly under the painful area it can make symptoms worse, so position matters. Custom insoles may be recommended for some people.
- Avoid high heels and flat, flimsy shoes. Heels push weight onto the forefoot and bend the toes upwards; very soft, flexible shoes give little protection. Avoid walking barefoot on hard floors while symptoms settle.
- Activity modification. Reduce running, jumping, lunging and long periods of standing. Cycling (with a stiff-soled shoe), swimming and upper-body exercise are good ways to stay active.
- Ice and elevation can help with flare-ups of pain and swelling.
- Anti-inflammatory medication. A short course of anti-inflammatory tablets or gel may help with pain, if they are suitable for you. Check with your GP or pharmacist first, particularly if you have stomach, kidney or heart problems or asthma.
- Steroid injections: used with caution. Steroid can weaken ligament tissue and may increase the risk of the plantar plate tearing further or the toe drifting. For this reason steroid injections are used very selectively, if at all, and Mr Hester will discuss the risks and benefits with you.
- Walking boot. For a particularly painful flare, a short period in a walking boot is sometimes advised to rest the forefoot.
Helpful
- Taping the toe level or pointing slightly down
- Daily calf stretches
- Stiff-soled or rocker-soled footwear
- A metatarsal pad just behind the ball of the foot
- Cycling and swimming to stay active
Avoid while it settles
- Bending the toes backwards, including toe or plantar fascia stretches and kneeling with the toes tucked under
- Calf raises, lunges, skipping and deep squats on the balls of the feet
- High heels and thin, flexible shoes
- Walking barefoot on hard floors
What timescales should I expect?
Ligament tissue heals slowly, and plantar plate injuries need patience. Many people notice the pain beginning to ease over the first few weeks once the toe is taped and the foot is properly offloaded. Treatment is usually continued for several weeks after that, and it usually takes three to six months for symptoms to settle fully, and occasionally up to a year. Returning gradually to sport and normal footwear helps avoid setbacks. If there is little or no improvement despite a dedicated period of non-surgical treatment, or the toe keeps drifting, Mr Hester will review the options with you.
| Stage | What it typically involves |
|---|---|
| Early (first weeks) | Taping, stiff-soled footwear, metatarsal pad, reduced impact activity, daily calf stretches. Pain usually starts to ease. |
| Middle (around 6–12 weeks) | Continue offloading and stretching. Taping is gradually reduced if the toe stays in a good position. Low-impact exercise is built up. |
| Later (3–6 months, sometimes longer) | Gradual return to normal footwear and higher-impact activity as comfort allows. Review if symptoms persist. |
These are general guides only. Everyone's recovery is different, and Mr Hester will tailor the plan to you.
Surgery and recovery
Surgery is considered when pain continues despite a good period of non-surgical treatment, when the toe is becoming increasingly unstable or deformed, or when a crossover toe has developed.
Plantar plate repair involves direct surgical repair of the torn ligament through a small incision on the top or sole of the foot. The plantar plate is reattached and any associated bony deformity or metatarsal length discrepancy is corrected at the same time.
In some cases, a Weil osteotomy (shortening of the metatarsal) is performed alongside the repair to reduce tension on the joint and improve healing. Associated hammer toe deformity may also be corrected at the same time.
Surgery is performed as a day case under general anaesthetic.
Recovery after surgery
| Timeframe | What to expect |
|---|---|
| 0–2 weeks | Rest, foot elevated. Post-operative shoe. Wound kept dry. |
| 2 weeks | Wound review. Sutures trimmed or removed. Continue post-op shoe. |
| 2–6 weeks | Walking in post-op shoe. Toe may be strapped to maintain alignment. |
| 6–8 weeks | Transition to wide, supportive trainer. Physiotherapy begins. |
| 8–12 weeks | Gradual return to normal activity. Swelling may persist. |
| 3–6 months | Return to sport and full activity if healing is complete. |
Frequently Asked Questions
Items patients often find useful in the first two weeks. Always follow your surgical team's instructions; these are general suggestions, not medical advice. As an Amazon Associate I earn from qualifying purchases.عناصر يجدها المرضى مفيدة غالباً في الأسبوعين الأولين. اتبع دائماً تعليمات فريقك الجراحي؛ هذه اقتراحات عامة وليست بديلاً عن المشورة الطبية. بصفتي شريكًا في برنامج Amazon Associates، أحصل على عمولة من عمليات الشراء المؤهلة.
As an Amazon Associate I earn from qualifying purchases. These are general suggestions, not a substitute for advice from your surgical team.بصفتي شريكًا في برنامج Amazon Associates، أحصل على عمولة من عمليات الشراء المؤهلة. هذه اقتراحات عامة، ولا تغني عن نصيحة فريقك الجراحي.
To discuss your symptoms with Mr Hester, please get in touch to arrange a consultation. Appointments are available privately in central London and in the NHS at King's College Hospital.
Book a ConsultationCall 020 7046 8004. Private clinics at Devonshire Place, Cromwell Road, London Bridge and King Edward VII's Hospital.
This page provides general information and is not a substitute for personal medical advice. If you have diabetes, reduced sensation or circulation problems in your feet, or sudden severe pain, swelling or redness, please seek medical advice promptly.